A key coenzyme in energy metabolism, DNA repair and cellular signalling
Overview
NAD+ is a coenzyme, not a peptide. Its full name is Nicotinamide Adenine Dinucleotide, and it consists of two nucleotides joined together. While it sits appropriately among the research-molecule pages on this site, it would be scientifically inaccurate to call it 'the peptide NAD+'. Present in every cell, NAD+ takes part in two principal kinds of activity. The first is electron transfer within energy-producing processes: NAD+ is the oxidised form, and on accepting electrons and hydrogen it becomes NADH. The balance between the two influences glycolysis, the Krebs cycle, the respiratory chain and further metabolic pathways. The second role is as a substrate for enzymes, including the Sirtuins, the PARP proteins involved in responding to DNA damage, and CD38, an enzyme that participates in cellular signalling and in NAD+ breakdown. When these enzymes consume NAD+, the molecule does more than carry electrons: it is broken down as part of the biological reaction itself [1-3]. Research interest in NAD+ grew following studies connecting NAD balance with mitochondrial function, inflammation, cellular stress and ageing. Most of the strongest findings on age-related decline, and on improvement after NAD levels were raised, come from animal work, however. Human data are more nuanced and vary with the tissue, the population and the measurement method. (PubMed)
Biological Mechanism
During energy production, NAD+ accepts electrons from molecules being broken down within the cell and becomes NADH. NADH can then pass those electrons to the mitochondrial respiratory chain, where they help generate a proton gradient and produce ATP. This does not mean that more NAD+ invariably yields more energy: mitochondrial activity also depends on oxygen, nutrient availability, enzyme function, the NAD+/NADH ratio and the overall state of the cell [1]. The Sirtuin family uses NAD+ in deacetylation reactions that modify proteins involved in metabolism, damage repair and the stress response. PARP enzymes use it to build ADP-ribose chains as part of the DNA-damage response, and CD38 breaks NAD+ down to generate signalling molecules linked, among other things, to calcium and immune function [2,3]. Mouse studies found that CD38 activity rises with age and contributes both to falling tissue NAD levels and to changes in mitochondrial function. A further study proposed a connection between the accumulation of senescent cells, the release of inflammatory signals, an increase in CD38-expressing macrophages and declining NAD in liver and adipose tissue [2,3]. This model offers one possible mechanism through which inflammation and cellular ageing influence NAD balance. It does not demonstrate that every older adult has a systemic 'NAD+ deficiency', nor does it establish that artificially raising NAD would alter the ageing process as a whole. (PubMed)
Research Evidence
Preclinical evidence on the NAD system is extensive, spanning models of metabolism, muscle, brain, inflammation and ageing. In certain models, raising NAD via precursors, or by reducing the activity of enzymes that consume it, improved metabolic and functional measures. These findings helped drive human research, but they should not be taken as proof that the same effect occurs in humans. Nor is the assumption of a uniform, age-related decline in human NAD+ levels fully established. Earlier studies reported lower levels in some tissues and samples, yet a study published in Nature Metabolism in 2026 measured whole-blood NAD+ across seven human cohorts and found levels to be relatively stable across age and across several lifestyle interventions. The authors concluded that whole-blood NAD+ is not necessarily a good marker of ageing [4]. This does not flatly contradict the animal tissue studies. Whole blood, muscle, liver, brain and adipose tissue are distinct biological compartments, and red blood cells hold a large metabolic pool capable of masking changes taking place in other tissues. The finding underlines the need to state which tissue was measured, and by what method, rather than referring to 'the NAD level in the body' as if it were one uniform figure. (PubMed)
The Difference Between NAD+, NADH, NR and NMN
Discussion of NAD often draws in several distinct molecules. NADH is the reduced form of NAD+, whereas NR and NMN are precursors that the body can feed into NAD-synthesis pathways. Although metabolically connected, they are separate substances with differing pharmacokinetics. A randomised study in middle-aged and older adults found that Nicotinamide Riboside, or NR, raised the blood NAD metabolome and was well tolerated over the study period [5]. In a separate controlled study of 12 older men, NR increased NAD-related metabolites in muscle but did not improve the mitochondrial bioenergetics that were measured [6]. A randomised study in postmenopausal women with prediabetes and overweight reported that NMN improved muscle insulin sensitivity and certain signalling pathways, without a parallel improvement across every glucose measure or every organ [7]. These studies help clarify the NAD system, but they do not constitute direct evidence regarding NAD+ infusion. A precursor that is ingested and then metabolised in the gut, liver and tissues is not equivalent to the NAD+ molecule located outside cells, and even two substances that raise the same NAD-related marker may differ in duration of activity, distribution and functional outcome. (PubMed)
Direct Evidence on IV NAD+
Direct human literature on NAD+ infusion is far thinner than that on NR and NMN. A 2019 pilot study followed NAD+ and its metabolites in plasma and urine over a prolonged infusion; its purpose was to characterise metabolism and clearance, not to evaluate treatment of ageing, fatigue, cognition or any specific disease [1]. In the first hours, plasma NAD+ did not show a simple, immediate rise proportional to the amount administered. Changes in NAD and related metabolites emerged later, together with urinary excretion, which suggests that part of the substance is broken down or rapidly metabolised before it appears in the blood as intact NAD+. The study was small and does not reveal which tissues the substance reached or whether any clinical benefit resulted [1]. A small retrospective study published in 2026 reviewed real-world data on NAD+ and NR infusions in a commercial setting. Among NAD+ recipients it documented gastrointestinal symptoms, raised heart rate, chest pressure and discomfort during the infusion. Being non-randomised, lacking a placebo and relying on a small number of records, it offers preliminary tolerability information rather than proof of efficacy or a complete safety profile [8]. (PubMed)
NAD+, Ageing and Outcome Measures
Measuring NAD alone is not enough for ageing research. Even where an intervention raises blood NAD+ or muscle metabolites, it remains necessary to ask whether mitochondrial function, insulin sensitivity, strength, endurance, cognition, morbidity or quality of life have actually changed. Ageing encompasses DNA damage, epigenetic change, chronic inflammation, impaired communication between cells, protein alterations, declining stem-cell function and mitochondrial changes. NAD+ connects with several of these axes but does not govern the system on its own, so presenting it as an 'anti-ageing molecule' stretches the conclusions beyond what the evidence supports. The direction of causality is not always clear, either. Lower NAD in a diseased tissue could contribute to the disease, but it might equally result from inflammation, cellular damage or a shift in cell composition, and raising the marker offers no guarantee that the underlying cause has been addressed. (PubMed)
Safety, Sterility & Endotoxins
Assessing the safety of an injectable NAD+ product involves more than confirming the identity of the molecule. A sterile product must satisfy requirements covering raw material, sterility, endotoxins, particulates, concentration, stability and storage, and material intended for food or supplement use is not automatically suitable for preparing one. In October 2024 the FDA reported on the use of food-grade NAD+ raw material to prepare intravenous products. The agency had received reports of severe chills, tremor, vomiting and fatigue, with some patients needing medical care, and described the reaction as consistent with exposure to high levels of endotoxins [9]. In a warning letter dated January 2026, the FDA described an incident in which three people were referred to the emergency room after receiving an NAD+ product from the same batch; testing of a sealed vial found an endotoxin level of 3,360 EU per mL [10]. These events do not show that every reaction to an NAD+ infusion stems from endotoxins, or that the molecule itself necessarily provokes the same reaction. What they do show is that differences in raw-material quality and production control can materially alter the risk, and that a contaminated product makes it impossible to judge the safety of pure NAD+. (U.S. Food and Drug Administration)
Translation Limitations & Quality Metrics
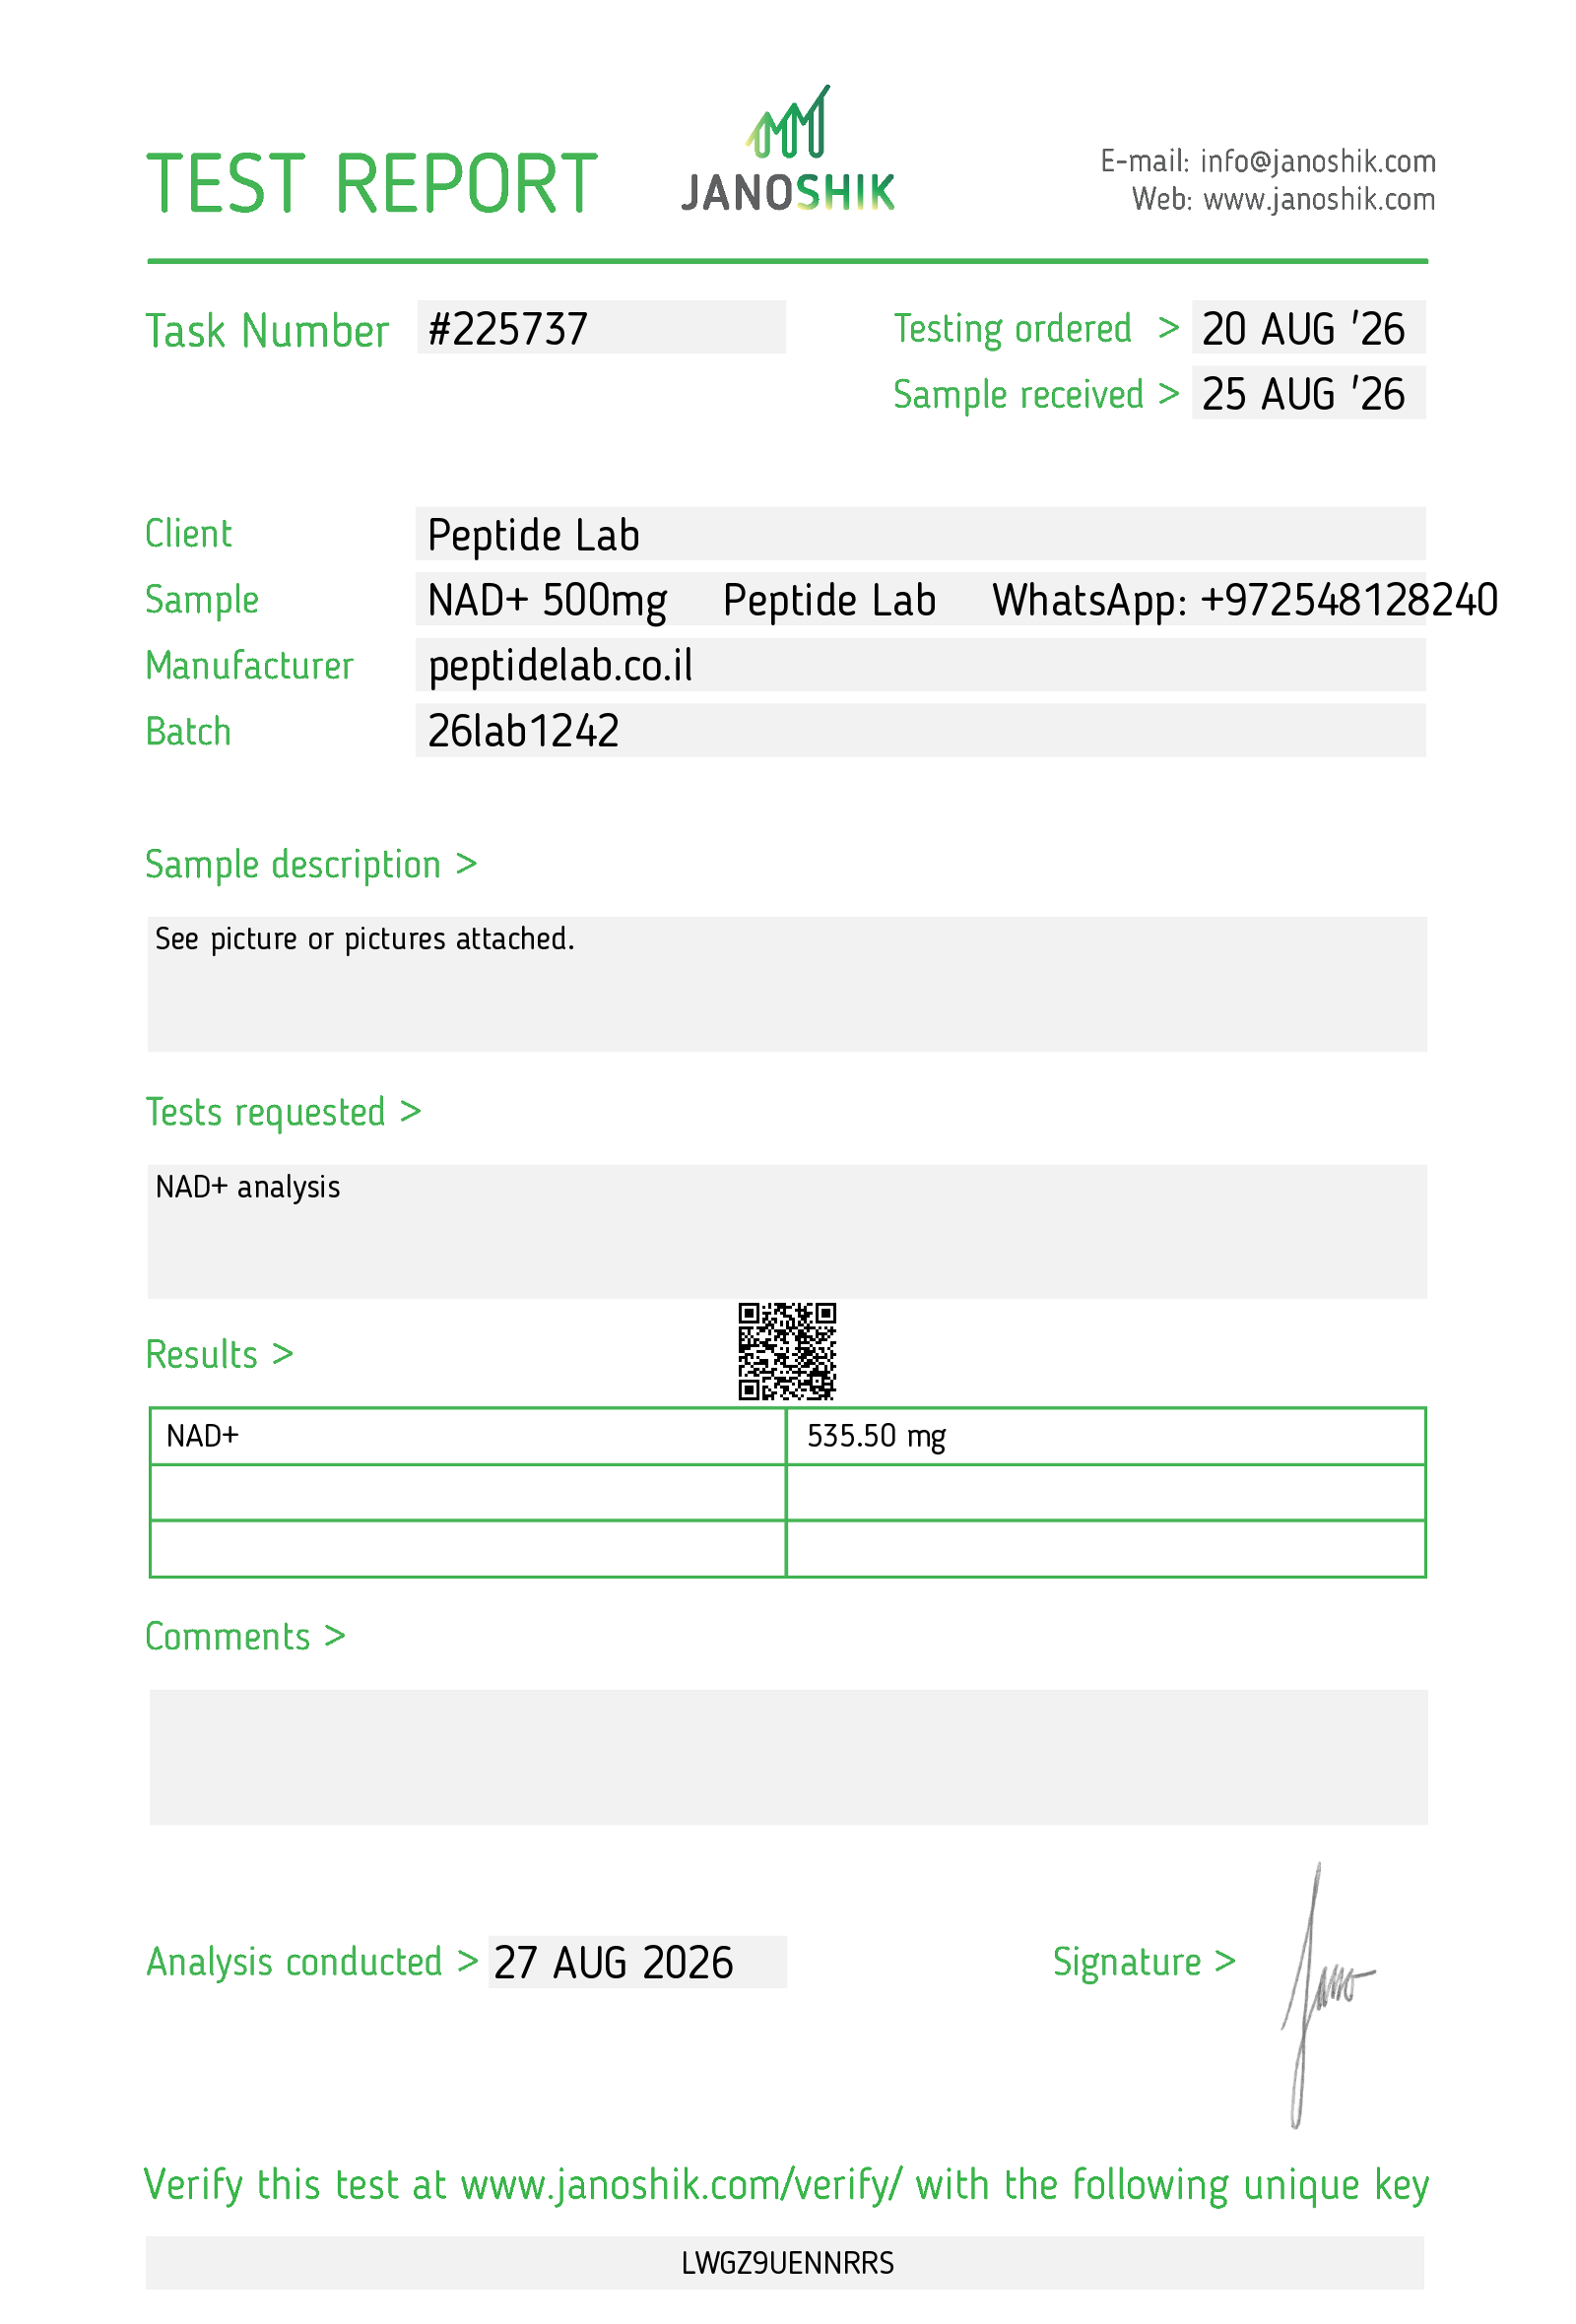
A central limitation in this field is the tendency to equate raising NAD with a medical effect. A study showing a metabolite increase after NR does not demonstrate improved function, and a study on NMN does not show that an NAD+ infusion would produce the same outcome. Blood measurements, moreover, do not necessarily reflect what is happening in the liver, muscle or brain. Precise characterisation of the test substance is equally essential. NAD+ is susceptible to breakdown, hydrolysis and oxidation, and its measurement is sensitive to how samples are collected, the time before freezing and the laboratory method used. A finished product calls for testing of identity, concentration, degradation products, sterility and endotoxins. Future research on NAD+ itself should incorporate a control group, blinding, functional outcomes and safety monitoring; without these elements, it is hard to distinguish genuine biochemical activity from an expectation response, the effect of the infusion fluids, or short-lived changes that do not persist.
Summary
NAD+ is a key coenzyme in energy transfer, cellular signalling and the activity of enzymes involved in DNA repair and the stress response [1-3]. Research has linked NAD levels with inflammation and ageing, but the human data are inconsistent, and direct evidence on infusion is confined to small studies, set against unresolved questions of safety, sterility and endotoxins [2-10]. This material is supplied for laboratory research use only.
Selected Research Sources
- Grant R. et al. A Pilot Study Investigating Changes in the Human Plasma and Urine NAD+ Metabolome During a Six-Hour Intravenous Infusion of NAD+. Frontiers in Aging Neuroscience, 2019. PMID: 31572171
- Camacho-Pereira J. et al. CD38 Dictates Age-Related NAD Decline and Mitochondrial Dysfunction through an SIRT3-Dependent Mechanism. Cell Metabolism, 2016. PMID: 27304511
- Covarrubias A.J. et al. Senescent cells promote tissue NAD+ decline during ageing via the activation of CD38+ macrophages. Nature Metabolism, 2020. PMID: 33199924
- Trętowicz M.M. et al. Human whole-blood NAD+ levels do not vary with age or lifestyle interventions. Nature Metabolism, 2026. PMID: 42135539
- Martens C.R. et al. Chronic nicotinamide riboside supplementation is well tolerated and elevates NAD+ in healthy middle-aged and older adults. Nature Communications, 2018. PMID: 29599478
- Elhassan Y.S. et al. Nicotinamide Riboside Augments the Aged Human Skeletal Muscle NAD+ Metabolome and Induces Transcriptomic and Anti-inflammatory Signatures. Cell Reports, 2019. PMID: 31412242
- Yoshino M. et al. Nicotinamide mononucleotide increases muscle insulin sensitivity in prediabetic women. Science, 2021. PMID: 33888596
- Reyna K. et al. Intravenous infusion of nicotinamide adenine dinucleotide and nicotinamide riboside: a retrospective real-world pilot study. Frontiers in Aging, 2026. PMID: 41704678
- U.S. Food and Drug Administration. FDA Reminds Compounders to Use Ingredients Suitable for Sterile Compounding. 2024. FDA.gov
- U.S. Food and Drug Administration. Warning Letter to GenoGenix LLC. January 20, 2026. FDA.gov




Reviews
There are no reviews yet.